Open-Access Medical Paper Appraisal, NNT & Absolute Risk Desk
When a clinical trial press release announces that a new drug cuts cardiovascular or cancer events by 50%, what does that actually mean for you or someone you love? If the 5-year event rate in the untreated placebo group was 0.2% (2 in 1,000) and dropped to 0.1% (1 in 1,000), the relative risk reduction is indeed 50%, yet the true absolute risk reduction is just 0.1%, requiring 1,000 treated patients (NNT = 1,000) to prevent a single event.
Med-Read.org is an independent clinical methodology mentor and open-access study appraisal desk. Sit down with our interactive calculators and per-1,000 evidence tables to see through statistical spin before making a healthcare decision.
Most medical headlines report Relative Risk Reduction (RRR), which magnifies small effects when baseline disease incidence is low. To evaluate any clinical trial or environmental cohort accurately, always convert relative percentages into Absolute Risk Reduction (ARR = Control Event Rate minus Experimental Event Rate) and Number Needed to Treat (NNT = 1 divided by ARR) over a defined follow-up horizon.
Patients Before P-Values: Statistical significance (p < 0.05) only measures how unlikely an observation is under random chance alone, not whether a treatment meaningfully helps a human life. Never discontinue prescribed cardiovascular, metabolic, or oncology therapy based on a single study without consulting your treating physician.
The Medical Headline De-Spinner & 1,000-Person Reality Lens
Click a landmark clinical trial preset below or adjust the Control Event Rate (CER %) and Experimental Event Rate (EER %) to see how many people out of 1,000 actually benefit:
Events prevented by therapy: 15Event occurs despite therapy: 65Event-free either way: 920
-18.8%
Headline Relative Risk (RRR)
What press releases emphasize
-1.50% (15 / 1,000)
True Absolute Difference (ARR)
Actual probability shift per patient
67
Number Needed to Treat (NNT)
Patients treated to prevent 1 event
985 / 1,000
Unchanged Outcome Cohort
Same outcome whether treated or not
Over 3.3 years, you must treat 67 patients (NNT = 67) to prevent 1 clinical event (15 people helped per 1,000 treated; 65 still experience an event despite treatment; 920 remain event-free either way).
Select Study Design to Inspect Methodological Rules
Randomized Controlled Trial (RCT) with Hard Clinical Endpoints
HIGH CERTAINTY · GRADE A
Concealed randomization balances both known and unknown baseline confounders. When an adequately powered multi-center RCT demonstrates a statistically and clinically meaningful reduction in all-cause mortality, organ failure, or validated patient quality of life under Intention-to-Treat (ITT) analysis, it warrants practice-changing clinical confidence.
Trials Powered Only on Surrogate Biomarkers or Imaging
SURROGATE ONLY · VERIFY OS
Many FDA and EMA accelerated approvals rely on laboratory or radiographic surrogates: shrinking a tumor on CT scan (Progression-Free Survival), lowering HbA1c by 0.5%, or clearing amyloid plaques. Across oncology and cardiology history, over half of surrogate improvements fail to extend Overall Survival (OS) or improve patient symptoms due to off-target toxicity.
For exposures that cannot ethically be randomized, such as urban road traffic noise (dB Lden), air particulate matter (PM2.5), or occupational toxins, large prospective cohorts provide vital dose-response curves. However, single-food or supplement observational studies with Hazard Ratios between 0.80 and 1.30 are frequently driven by socioeconomic and healthy-user confounding.
Unverified Open-Access PDFs, Paper Mills & P-Hacked Case Series
HIGH BIAS · DO NOT CITE
An open-access PDF indexed in Google Scholar or deposited in PubMed Central (PMC) via author manuscript upload is not automatically vetted by MEDLINE's Literature Selection Technical Review Committee. Watch for turnaround times under 14 days from submission to acceptance, missing ClinicalTrials.gov (NCT) registration, and post-hoc subgroup p-values.
Comparing media-reported relative risk figures against true per-1,000 absolute differences and methodological certainty across major medical specialties.
Relative Risk Reduction (RRR) vs. Absolute Risk Reduction (ARR) & NNT Across Clinical Domains
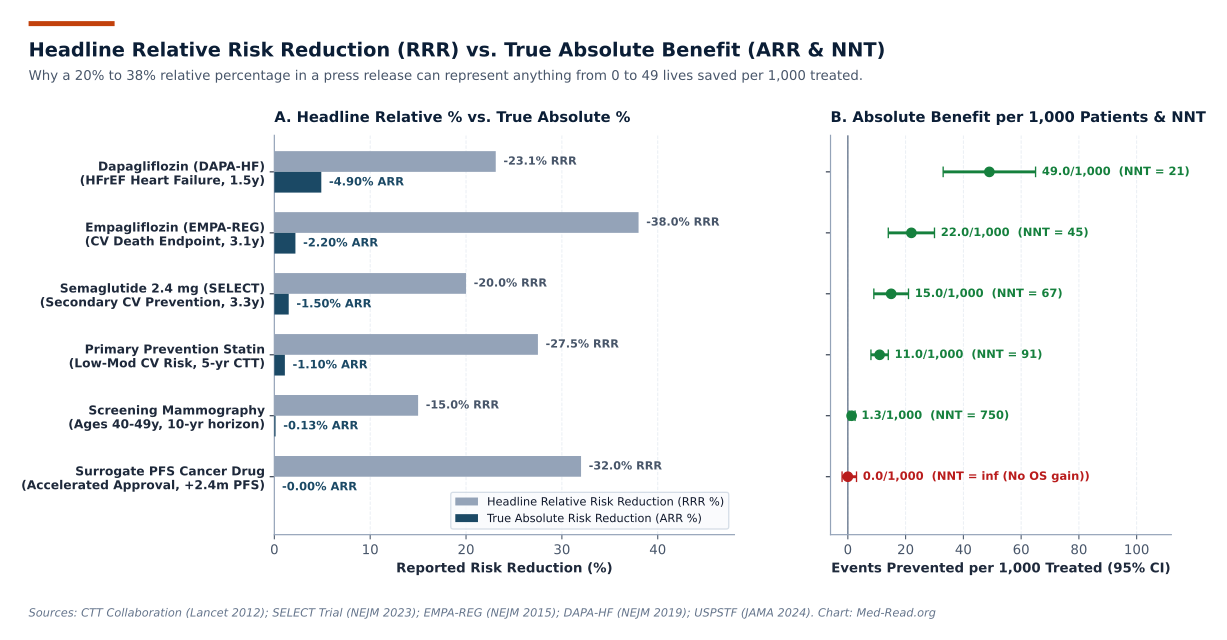
The Two-Track Risk Lens: How Identical 50% Relative Reductions Hide a 100-Fold Difference in Benefit
Without the baseline event rate in the untreated control group, a Relative Risk Reduction (RRR) is mathematically incomplete.
Figure 1 (Our World in Data / Lancet Style Synthesis): Comparing media-reported Relative Risk Reduction (RRR %) against true Absolute Risk Reduction (ARR %) and events prevented per 1,000 patients across six landmark interventions.
01. How to Read a Medical Paper in 10 Minutes
METHODOLOGY CORE
A step-by-step clinical checklist for dissecting randomized trials, observational cohorts, hazard ratios, confidence intervals, and p-hacking red flags.
Core Tools
CER/EER to NNT table, CONSORT 2025 checklist, Confounding matrix
Target Reader
Patients, clinicians, and health journalists verifying study claims
Why indexing in PubMed Central (PMC) differs from MEDLINE curation, how to verify Crossref DOIs and DOAJ standing, and how to spot paper-mill fabrications.
Core Tools
PMC vs. MEDLINE vs. DOAJ matrix, 5-step DOI & NCT audit
03. Environmental Noise Exposure & Cardiovascular Health
WHO & HW.AC.UK MONOGRAPH
Dedicated acoustic epidemiology monograph honoring the historical Heriot-Watt University and SCIRP citations on peri-urban noise exposure (dB Lden / Lnight) and cardiovascular risk.
Thresholds
WHO Road Traffic 53 dB Lden / 45 dB Lnight; +8% IHD risk per +10 dB
Archival Anchor
Preserves MedRead MS-946 & MS-959 (Zia MA et al., 2020)
Common Questions from Patients, Clinicians & Researchers
Candid, plain-language answers grounded in CONSORT 2025, GRADE, WHO guidelines, and per-1,000 outcome arithmetic.
What is the difference between relative and absolute risk in a medical study?
Relative risk compares the ratio of probabilities between two groups (for example, cutting risk from 2% to 1% is a 50% relative reduction), whereas absolute risk difference subtracts one rate from the other (2% minus 1% equals a 1% absolute reduction, or 10 fewer events per 1,000 people). Only absolute risk tells you your actual likelihood of benefiting.
Why does med-read.org preserve historical 2019-2022 open-access monograph records?
Between 2019 and 2022, MedRead Publishing Group published open-access articles on environmental noise exposure, pediatric nutrition integration, and polypharmacy that were cited by the World Health Organization (WHO EMRO), Heriot-Watt University, SCIRP, and Auctores. Maintaining permanent semantic concordance anchors prevents broken academic citations and updates those findings with 2024-2026 evidence.
Does a p-value below 0.05 prove that a medical treatment works?
No. A p-value below 0.05 only indicates that the observed difference would occur less than 5% of the time if the null hypothesis were true and there were zero bias. In large trials, tiny clinically irrelevant changes can achieve p < 0.05, while in small or p-hacked studies, selective reporting produces false-positive p-values.